

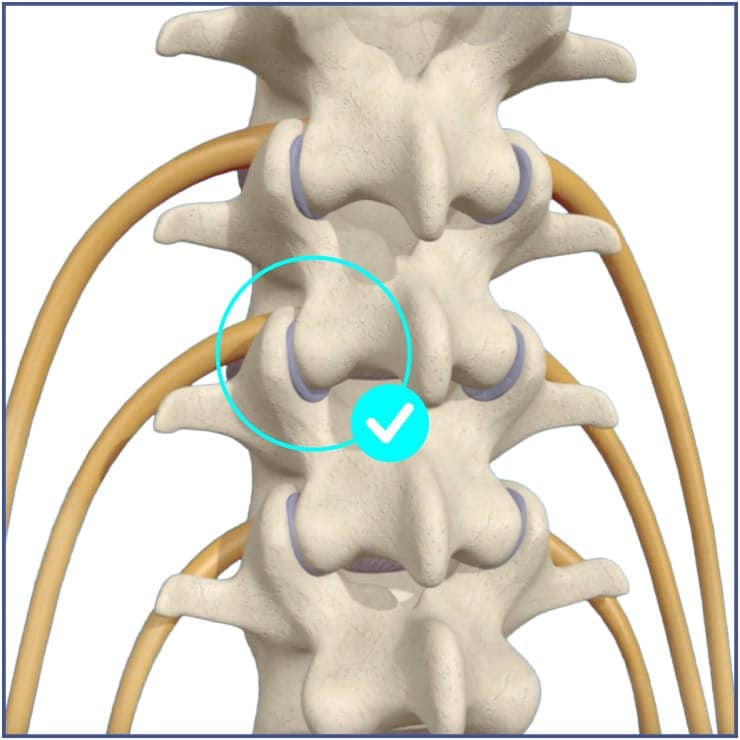
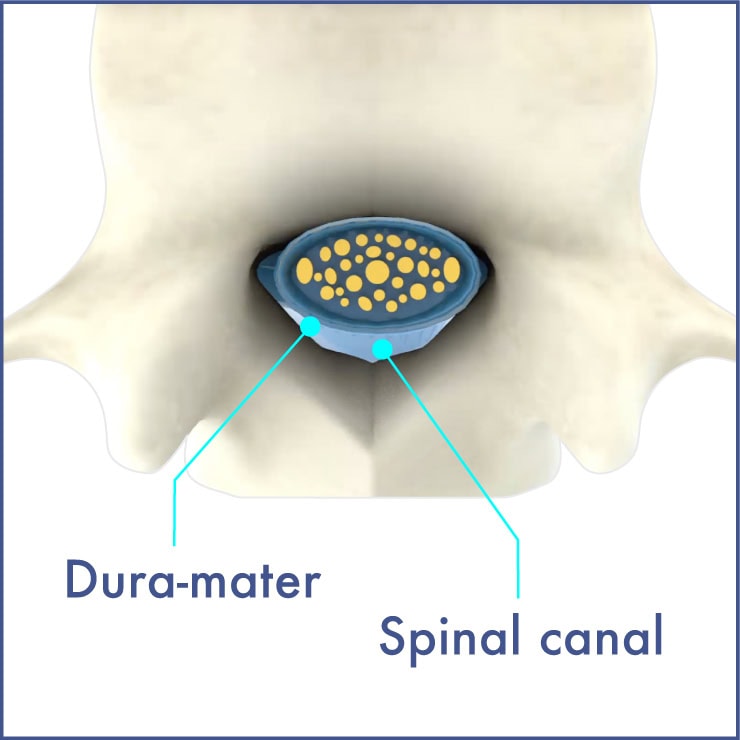
No canal arthrosis, facet capsule with synovial fluid allowing smooth facet joint and spinal motion

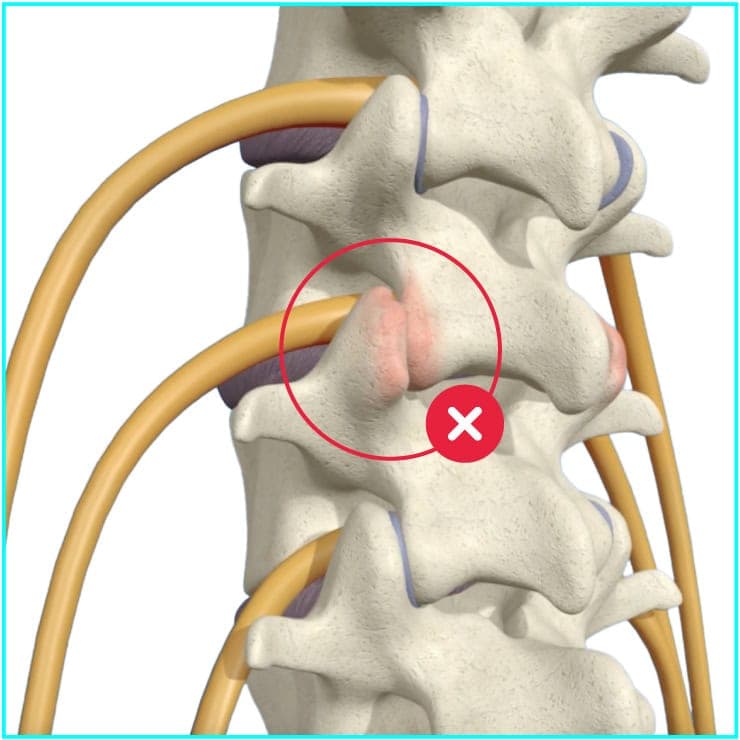
Little fluid left in the facet capsule, the resulting friction causes inflammation and back pain, typically worse when bending backward, twisting or holding a position for long.


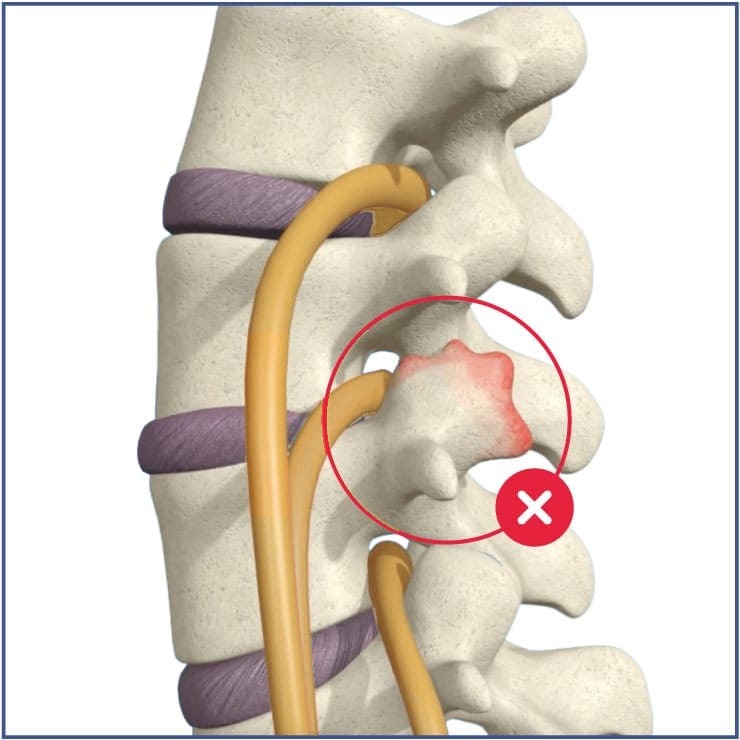
As the facet joints wear, the spinal segment can move more than it should. The pain becomes mechanical: it comes in recurrent episodes, sometimes with a feeling that the back is “giving way”.

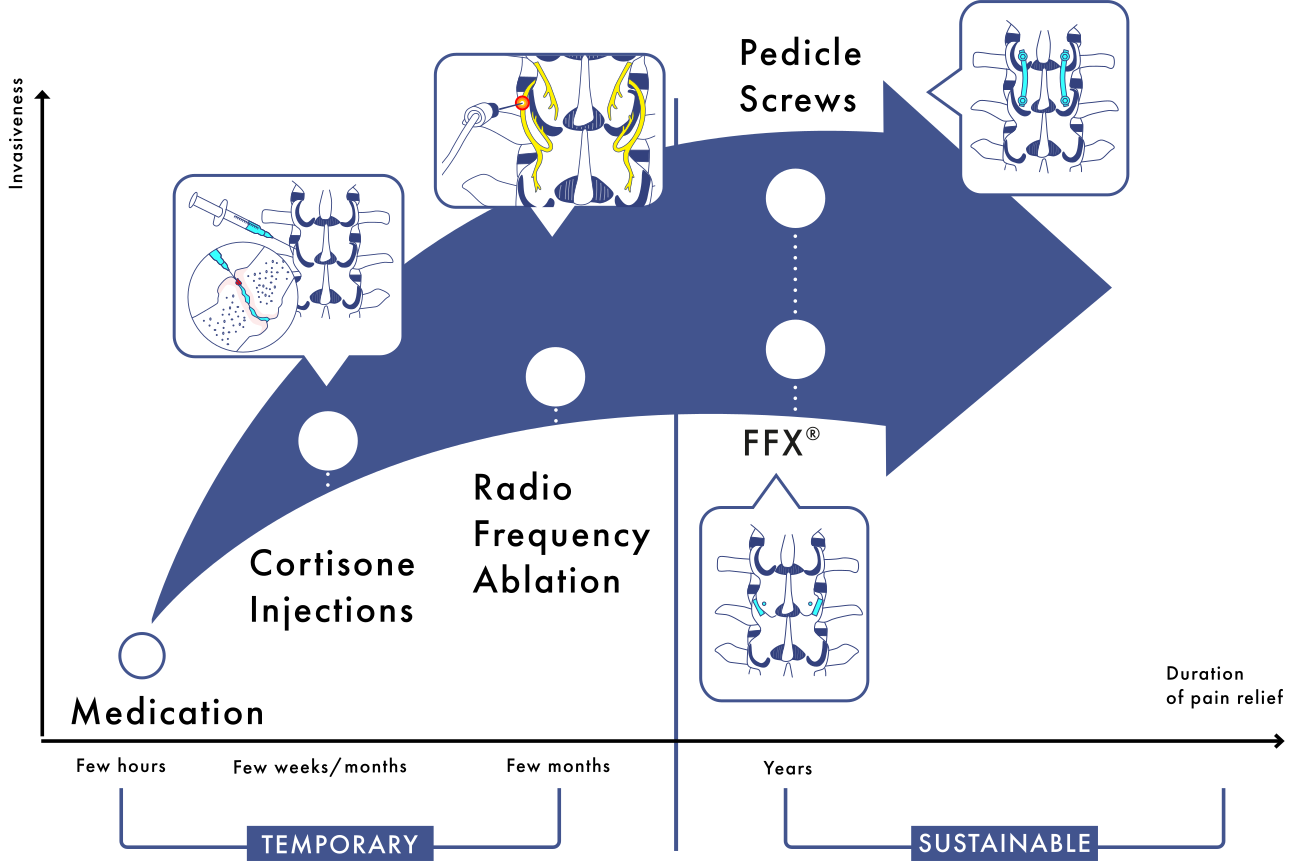
Cortisone injections to reduce facet joint inflammation

Temporary thermal
destruction of pain nerves
in the facets

Fusion of the painful facet joints with FFX® facet cages, to stop the motion causing pain
As the facet joints wear, the spinal segment can move more than it should. The pain becomes mechanical: it comes in recurrent episodes, sometimes with a feeling that the back is “giving way”.
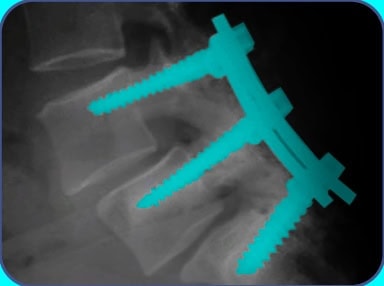
Conventional fusion: Pedicle screws inserted into each vertebra of the treated segment and connected by rods.
It remains necessary for major instability or deformity.
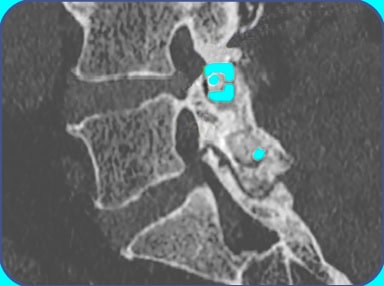
A titanium facet cage placed in each facet joint and secured with an FFX® locking screw, with bone graft.
It is intended to fuse the facet joints only, without Pedicle screws or rods, with 19 times less implanted metal.
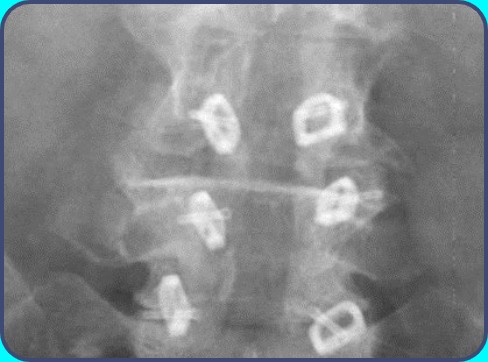
FFX® is FDA cleared for lumbar degenerative disc disease and/or degenerative facet disease with instability, from L3 to S1, in skeletally mature patients who have failed conservative care.
It is not suitable for every patient, for example in case of osteoporosis or spondylolisthesis of grade II or higher. Talk to your spine physician.
Chronic low back pain can come from several structures: the intervertebral discs, the facet joints, the sacroiliac joints, the nerves and the muscles. The facet joints are the source of pain in up to 45%Perolat et al., Insights Imaging, 2018 pubmed.ncbi.nlm.nih.gov/30090998/
Manchikanti et al., Pain Physician, 2008 pubmed.ncbi.nlm.nih.gov/18196171/ of people with chronic low back pain. Facet joint pain is often overlooked, because imaging alone cannot confirm it.
Yes, and they are among its most common sources, involved in up to 45%Perolat et al., Insights Imaging, 2018 pubmed.ncbi.nlm.nih.gov/30090998/
Manchikanti et al., Pain Physician, 2008 pubmed.ncbi.nlm.nih.gov/18196171/ of cases. Wear of the facet joint reduces its lubricating fluid; the resulting friction causes inflammation and pain, typically in the lower back, often worse when standing, twisting or bending backward. These clinical symptoms suggest facet joint pain but cannot confirm it on their own. Over time, facet degeneration can also make a spinal segment unstable.
Imaging alone cannot confirm that the facet joints are the source of pain, because a significant proportion of people without back pain also show degenerative changes of the facet joints on CT scans or MRIBrinjikji et al., AJNR Am J Neuroradiol, 2015 www.ajnr.org/content/36/4/811. The reference test is a diagnostic block: a local anesthetic is injected into the facet joint or near its small nerves (e.g., medial branch block). If the pain clearly decreases for a few hours, the facet joint is considered the pain generatorCohen et al., Reg Anesth Pain Med, 2020 (multispecialty consensus guidelines) pubmed.ncbi.nlm.nih.gov/32245841/. Your physician interprets the result together with your symptoms, examination and imaging. To look for instability, your physician may order flexion and extension X-rays.
Treatment follows steps, from the least to the most invasive: pain medication and exercise-based physical therapy; corticosteroid injections, which reduce the painful inflammation locally, with an effect that typically lasts a few weeksCohen et al., Reg Anesth Pain Med, 2020 (multispecialty consensus guidelines) pubmed.ncbi.nlm.nih.gov/32245841/; then radiofrequency ablation, which uses heat to destroy the small nerves carrying the pain signal to the brain. Relief lasts several months, but the nerves typically grow back after 6 to 12 monthsSmuck et al., PM&R, 2012 (systematic review) onlinelibrary.wiley.com/doi/10.1016/j.pmrj.2012.06.007
Perolat et al., Insights Imaging, 2018 pubmed.ncbi.nlm.nih.gov/30090998/, so the procedure often has to be repeated. Surgery is considered only after conservative care has failed, and depends in particular on whether the spine is unstable.
Corticosteroid injections reduce inflammation inside or around the facet joint, but their relief is usually temporary (a few weeks)Perolat et al., Insights Imaging, 2018 pubmed.ncbi.nlm.nih.gov/30090998/
Cohen et al., Reg Anesth Pain Med, 2020 (multispecialty consensus guidelines) pubmed.ncbi.nlm.nih.gov/32245841/. Radiofrequency ablation uses heat to destroy the small nerves that carry the pain signal from the facet joint to the brain. It treats the signal, not its source: the worn joint itself is unchanged. The nerves typically grow back after 6 to 12 monthsSmuck et al., PM&R, 2012 (systematic review) onlinelibrary.wiley.com/doi/10.1016/j.pmrj.2012.06.007
Perolat et al., Insights Imaging, 2018 pubmed.ncbi.nlm.nih.gov/30090998/, so pain returns and the procedure often has to be repeated. When these treatments no longer bring lasting relief, your physician first reassesses the diagnosisCohen et al., Reg Anesth Pain Med, 2020 (multispecialty consensus guidelines) pubmed.ncbi.nlm.nih.gov/32245841/, including other possible causes of pain and spinal instability. Unlike these treatments, facet arthrodesis targets the source of the pain: it is intended to fuse the painful facet joints, so that the abnormal motion (micro-motion) that causes the inflammationVan Oosterwyck et al., Life, 2024 www.mdpi.com/2075-1729/14/11/1480 stops. Among its FDA-cleared indications, FFX® can be used as an aid to lumbar fusion, through bilateral immobilization of the facet joints at one or two levels with bone graft, for degenerative facet disease with instability from L3 to S1 in skeletally mature patients who have failed conservative care. Not every patient with facet joint pain has instability; your physician decides whether fusion is appropriate.
Facet arthrodesis (facet fusion) is a surgical procedure intended to fuse the painful facet joints so that they no longer move and rub. A facet joint is a small joint at the back of the spine, between two vertebrae. When it wears out, it moves abnormally with every step and every bending movement. These small abnormal movements (micro-motion) stretch the joint capsule and irritate the joint lining, which causes painful inflammationVan Oosterwyck et al., Life, 2024 www.mdpi.com/2075-1729/14/11/1480. Fusion means making two bones grow together into one solid bone. Once the joint is fused, it can no longer move, so the micro-motion and the inflammation it causes stop. To achieve this, the surgeon prepares the joint surfaces, adds bone graft and places a small implant that holds the joint still to promote new bone growth across it, much like a cast holds a broken bone to help it heal. FFX® is such an implant: a titanium facet cage placed inside each facet joint of the treated segment, on both sides, and secured with an FFX® locking screw. It provides temporary fixation and stabilization while fusion develops. It can be performed through open surgery or through minimally invasive approaches (tubular, endoscopic or fully percutaneous). Unlike conventional fusion with Pedicle screws and rods, it acts on the facet joints only. Fusion develops progressively: in three published studies, including a comparative study of selected patients undergoing decompression surgery, bony fusion was confirmed on imaging in 89% to 91% of casesMostofi, Eur J Orthop Surg Traumatol, 2025 (100 patients, 91% at 12 months) doi.org/10.1007/s00590-025-04425-y
Srour et al., Int J Spine Surg, 2020 (89% of devices used standalone, without PLIF, at 12 months) doi.org/10.14444/7149
Houari et al., Clin Spine Surg, 2025, published online 2024 (112 patients; 91% of patients with FFX® and its locking screw at 2+ years) pubmed.ncbi.nlm.nih.gov/39404118/ with FFX®, from one year to more than two years after surgery.
Conventional spinal fusion is intended to join two or more vertebrae so that they fuse into a single solid block of bone. It usually uses Pedicle screws, inserted into each vertebra and connected by rods, often with a cage placed in the disc space after removal of the disc. Whether there is an alternative depends on the cause of the pain, the stability of the spine and the patient's anatomy. Some options avoid fusion altogether, such as decompression alone when leg pain from compressed nerves predominates and the spine is stable. Others keep fusion but make it lighter: facet cage arthrodesis with FFX® is intended to fuse only the facet joints of the treated segment, without Pedicle screws, rods or removal of the disc, and uses 19 times less metal than a Pedicle screw construct. It remains a fusion, not an alternative to fusion. FFX® is FDA cleared for lumbar degenerative disc disease (back pain coming from a worn disc, confirmed by history and imaging) and/or degenerative facet disease with instability, from L3 to S1, in skeletally mature patients who have failed conservative care. It is not suitable for every patient: major instability or deformity still requires Pedicle screws.
In selected patients without major instability or deformity, FFX® can be used instead of Pedicle screws. In a retrospective comparative study of selected patients undergoing decompression surgery, surgery with FFX® was 35% shorter, with 44% less blood lossSrour, Cureus, 2022 (70 patients; 99 vs 153 min, 251 vs 447 mL) pubmed.ncbi.nlm.nih.gov/35399487/, than with Pedicle screws. In another comparative study, pain and function improved in both groups at more than two years, with no significant difference between themHouari et al., Clin Spine Surg, 2025, published online 2024 (112 patients; 91% of patients with FFX® and its locking screw at 2+ years) pubmed.ncbi.nlm.nih.gov/39404118/. Pedicle screws remain necessary for major instability or deformity. Talk to your spine physician about which technique suits your case.
FFX® is contraindicated in patients with osteoporosis or spondylolisthesis of grade II or higher; this list is not exhaustive. As with any spine surgery, potential risks include infection, bleeding, nerve injury, device loosening or migration, failure to achieve fusion and the need for additional surgery. Outcomes vary between patients. This summary does not replace the complete U.S. Instructions for Use, including all indications, contraindications, warnings and precautions. Discuss the expected benefits and risks with your treating spine surgeon.
Where do you live?